

IV vitamin therapy can be delivered safely, but only when three conditions hold together: a competent prescriber with a clear clinical indication, pharmacy grade or SOP driven sterile preparation, and monitored administration backed by genuine emergency readiness. Strip out any one of these and the risk profile changes substantially. This protocol is written for licensed practitioners, aesthetic prescribers and training academies, not for members of the public considering treatment.
TL;DR:
- Screen for component allergies, unstable heart or lung disease, renal impairment, pregnancy related cautions, and G6PD deficiency; check baseline bloodwork and medication interactions.
- Prefer pharmacy prepared products; unavoidable mixing requires a written prescription, trained staff, a clean area, single use devices, and patient labels with use deadlines.
- Use a pump with alarms and an in line filter no larger than 1.2 micrometres, and match cannula size to infusion concentration and volume.
- Record vital signs before, during, and after infusion, increasing checks for higher risk patients or unfamiliar formulations; repeat renal and electrolyte tests for repeat courses.
- Keep epinephrine, oxygen, and an AED accessible; train staff in anaphylaxis response and basic life support, and audit near misses and incidents through clinical governance.
Table of Contents
- A practical safety checklist before any IV vitamin infusion
- Patient assessment and contraindications
- Preparation and aseptic technique for IV vitamin infusions
- Administration technique: cannula, rate and device controls
- Monitoring during and after infusion, and recognising complications
- Compounding governance and pharmacy role
- Emergency preparedness and escalation
- Training, SOPs and documentation
- How to use our IV vitamin therapy safety toolkit
- Clinician responsibilities when patient demand runs ahead of protocol
- Where Mirror Pharma clinician resources fit into your protocol
- FAQ
- Sources
A practical safety checklist before any IV vitamin infusion
Most adverse events trace back to a step that was skipped, not a step that was done badly. A short, consistent checklist closes that gap far more reliably than memory or good intentions.
Before any infusion begins, confirm:
- A written prescription exists with a documented clinical indication, not a generic wellness request.
- Informed consent has been taken and recorded, including the risks of infusion reactions and vitamin toxicity.
- Baseline checks are complete: renal function, electrolytes, known allergies and, where relevant, G6PD status.
- The preparation has come from a licensed pharmacy wherever possible, with clear labelling and a defined time to use.
- The treatment area, infusion pump, filters and appropriate cannula are ready and checked.
- Emergency equipment, including an AED and anaphylaxis kit, is in date and accessible, with trained staff present.
- The episode is documented against the clinic’s standard operating procedure (SOP), with a clear route for incident reporting.
The Commission on Human Medicines guidance sets out that mixing medicines before administration should be avoided where possible, and when it cannot be avoided it must be prescribed in writing and carried out by competent staff under clear governance. That single principle underpins most of the checklist above.
Pro Tip: Keep the checklist as a physical or digital sign-off sheet attached to each patient record, not a poster on the wall. Audits consistently find gaps between what staff know and what they actually complete under time pressure.
Patient assessment and contraindications
Screening is where safety is won or lost long before the cannula goes in. A thorough history catches the patients who should never receive an infusion in the first place, or who need a modified approach.
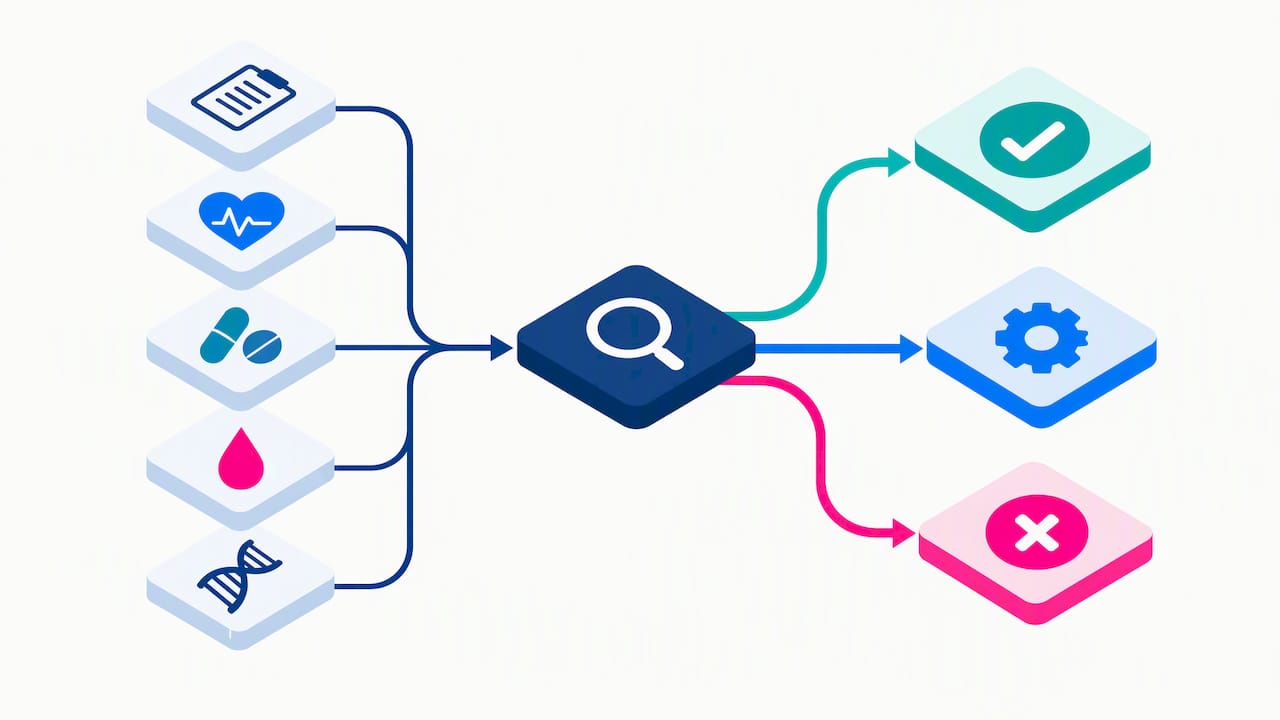
Absolute and relative contraindications include known hypersensitivity to any infusion component, unstable cardiac or respiratory disease, significant renal impairment, pregnancy (where caution rather than outright exclusion often applies, depending on indication), and G6PD deficiency, which raises the risk of haemolysis with certain ingredients.
Baseline blood tests worth requesting before treatment, and before repeat courses, typically include:
- Renal function and electrolytes, to rule out impaired clearance of high-dose vitamins and minerals.
- Full blood count, to establish a baseline before any infusion that carries haemolysis risk.
- Liver function tests, particularly where repeat or high-dose regimens are planned.
Medication interaction checks matter too. Anticoagulants, diuretics and certain supplements can all interact with infusion components, and any uncertainty should go to a pharmacist or the prescribing clinician before proceeding. For repeat infusions, monitoring frequency should scale with the patient’s risk profile rather than following a fixed calendar: a healthy patient on an occasional course needs less frequent review than someone with borderline renal function receiving regular treatment.
Preparation and aseptic technique for IV vitamin infusions
Preparation technique is where contamination and dosing errors are introduced, often invisibly, well before the infusion reaches the patient.
- Default to pharmacy-prepared or manufacturer-supplied products wherever they exist, rather than mixing on-site. The CHM mixing-of-medicines principles state this clearly: mixing should be avoided where possible, and when it is necessary, it must be prescribed in writing and carried out by a named competent person who accepts responsibility for the outcome.
- When near-patient mixing is unavoidable, follow the WHO injection safety toolkit, which calls for a designated clean preparation area, single-use devices, hand hygiene before each step, surface disinfection and safe disposal of sharps and waste.
- Label every near-patient preparation with the patient’s name, contents, preparation time and a defined window for use, and administer promptly rather than holding prepared syringes for later use on a different patient.
- Prepare one infusion for one patient at a time; batching preparations for multiple patients increases both labelling error and contamination risk.
- Use appropriate personal protective equipment, wipe vial septa and ampoule necks before each access, and use a one-hand technique for recapping needles where recapping is unavoidable.
This sequence turns a general principle into something a treatment room can actually run on a busy clinic day.
Administration technique: cannula, rate and device controls
Administration is where mechanical complications show up, and most of them are preventable with the right equipment choices rather than extra vigilance alone.
- Match cannula gauge to the infusion’s osmolarity and planned volume; a high-osmolarity vitamin infusion through an undersized cannula increases the risk of vein irritation and extravasation.
- Run the infusion through a pump with alarm settings enabled rather than free-flowing by gravity, particularly for larger volumes or less experienced staff.
- Use an in-line mechanical filter, generally a pore size no larger than 1.2 micrometres, during administration. A government device alert recommends in-line filtration during parenteral administration to reduce particulate and air embolism risk, and the same logic applies to high-volume vitamin infusions.
- Secure the cannula properly and check the site regularly during infusion for early signs of extravasation, swelling or pain that would warrant stopping.
Choosing the right cannula size for the infusion type and volume is a small decision with disproportionate consequences for patient comfort and safety.
Pro Tip: Prime the line and filter fully before connection to avoid introducing air, and never top up a running infusion bag; replace it with a freshly prepared one instead.
Monitoring during and after infusion, and recognising complications
Monitoring is not a single check at the start. It is a schedule that changes depending on the patient’s risk and the infusion’s composition.
- Record baseline vital signs before starting, then check at intervals through the infusion, more frequently for higher-risk patients or unfamiliar formulations.
- Repeat vital signs at the end of the infusion and again before discharge, documenting that the patient is stable.
- For patients on repeat courses or with borderline baseline results, repeat renal function and electrolyte testing rather than assuming stability.
- Recognise and act on red flags promptly: anaphylaxis, signs of haemolysis in a patient with G6PD deficiency, electrolyte disturbance, fluid overload or any suggestion of sepsis at the infusion site.
- Document the full episode, including observations and any deviation from the plan, and notify primary care where follow-up is clinically relevant.
High-dose IV vitamin infusions can bypass normal gastrointestinal regulation, which is why the Merck Manual specifically flags electrolyte imbalance, fluid overload and haemolysis in G6PD-deficient patients as recognised risks, and why routine use in otherwise healthy people is discouraged. The practical implication is that monitoring intensity should track the dose and the ingredient profile, not the length of the appointment slot.
Compounding governance and pharmacy role
Decisions about where and how an infusion is prepared sit at an organisational level, not just at the bedside.
- Commission pharmacy-made preparations for any combination that is not a licensed, ready-to-use product, reserving near-patient mixing for genuinely unavoidable situations.
- Maintain SOPs covering storage conditions, cold chain where relevant, labelling conventions, batch records and expiry handling for every preparation held on site.
- Run a documented risk assessment before approving any unlicensed combination locally, and route that assessment through clinical governance rather than individual clinician discretion.
- Assign senior management clear responsibility for medicines management, including scheduled audits of stock, storage and preparation records.
Our IV vitamin therapy safety toolkit was built to help clinics translate exactly this kind of governance into templates staff can actually use day to day.
Emergency preparedness and escalation
A clinic that offers IV vitamin infusions is making an implicit commitment to manage the rare but serious reaction, not just the routine appointment.
- Stock adrenaline, oxygen and an AED in every treatment area where infusions are given, checked on a defined schedule rather than left to chance.
- Ensure staff administering infusions hold current competency in anaphylaxis management and basic life support, with advanced life support training where the patient group warrants it.
- Agree clear transfer criteria in advance: which signs mean immediate call for emergency services, and what information gets handed over, including the infusion given, timing and observations.
- Review every emergency event through a formal post-event audit, feeding lessons back into the SOP rather than treating the incident as closed once the patient is safe.
Training, SOPs and documentation
Protocols only work if the people running them are assessed against them, not just handed a document to read once.
- Require a documented competency assessment before any staff member is authorised to administer IV vitamin infusions independently, repeated at defined intervals rather than as a one-off.
- Audit temperature logs, stock reconciliation and incident rates on a regular schedule, with a clear corrective action process when something falls outside range.
- Keep SOPs accessible at the point of care, not filed away, and review their content against current guidance at least annually.
- Feed every audit finding and incident report into clinical governance so that patterns are caught before they become harm.
Pro Tip: Treat a near-miss the same way you treat an actual incident for reporting purposes. Clinics that only log confirmed harm miss the early warning signs that matter most.
How to use our IV vitamin therapy safety toolkit
Our IV vitamin therapy safety toolkit gathers SOP templates, labelling templates, patient screening checklists and clinician guidance into one place, built around the governance principles set out above.
- Adopt the SOP templates into local policy, adjusting only the details specific to your clinic’s layout, staffing and equipment.
- Use the labelling templates for any near-patient preparation to meet the person-specific labelling and time-to-use requirements set out in the CHM guidance.
- Fold the competency checklist into existing staff training records rather than running it as a separate system.
- Review the IM/IV vitamins category and needles and consumables range as a starting point for procurement, subject to prescriber verification at checkout.
Clinician responsibilities when patient demand runs ahead of protocol
Demand for IV vitamin infusions has grown faster than the governance habits around them in plenty of clinics. That gap is where harm happens, not in the ingredients themselves.
A patient asking for an infusion is not the same as a patient who has a clinical indication for one, and the difference has to be made explicit in consent, not glossed over to meet demand. A standardised protocol, applied consistently, protects the patient more than any individual clinician’s experience or good intentions ever will on their own. Use the checklist. Resist the pressure to shortcut screening or monitoring because a treatment room is busy or a patient is insistent.
— Rizwan
Where Mirror Pharma clinician resources fit into your protocol
We built our clinician toolkit and product range around the same governance gap this article describes: clinics know the principles but need them translated into something usable on a working day. For licensed practitioners, that means SOP templates you can adopt without starting from a blank page, and a procurement process with prescriber verification built in rather than bolted on afterwards.
- Download the IV vitamin therapy safety toolkit for SOP and labelling templates aligned with the principles above.
- Browse the IM/IV vitamins category for products intended for clinician use, subject to verification.
- Check the needles and consumables range for the equipment your SOP requires, from cannulas to administration sets.
Access to prescription products is restricted to verified healthcare professionals and aesthetic practitioners; verification happens before any order ships.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
How safe is IV vitamin therapy?
IV vitamin therapy can be delivered safely when there is a genuine clinical indication, a competent prescriber, sterile preparation and proper monitoring throughout. Without those conditions, risks include infusion reactions, electrolyte imbalance and, in specific patient groups such as those with G6PD deficiency, haemolysis, as outlined by the Merck Manual.
What are the protocols for IV vitamin therapy?
A sound protocol covers patient screening and contraindications, pharmacy-led or SOP-governed preparation, controlled administration with appropriate filtration and monitoring, and a clear emergency pathway. The CHM mixing guidance and WHO injection safety toolkit set the governing principles behind most of these steps.
What are the 5 rules of IV administration?
Clinical IV administration guidance generally centres on confirming the right patient, right drug, right dose, right route and right time before any infusion begins, alongside the broader fluid and electrolyte monitoring set out in NICE/NHS IV fluid guidance. Definitions of the exact wording vary between institutions, so always check against your local SOP.
What should I avoid doing after an IV drip?
Avoid strenuous activity immediately after infusion until you are confident there is no delayed reaction, and seek medical review promptly if you notice swelling, pain or redness at the cannula site. Report any symptoms suggesting an allergic reaction or unusual fatigue to the prescribing clinician rather than waiting for a routine follow-up.
Sources
- Mixing of medicines prior to administration in clinical practice: medical and non-medical prescribing (CHM / DH guidance)
- Principles and protocols for intravenous fluid therapy (NICE/NHS guidance)
- WHO injection safety and best practices toolkit
- Intravenous Vitamin Therapy (Myers’ Cocktail) – Merck Manual
- Gov