
Choosing the right dermal filler for different treatment areas comes down to matching rheology, not brand, to the job the tissue needs done: high G’ hyaluronic acid (HA) for periosteal structure in the cheeks, jawline and chin, medium G’ for midface contouring, and low G’ cohesive HA for mobile, superficial zones like the lips. In vascular danger zones (nose, glabella, tear trough) reversibility should outweigh longevity every time, since hyaluronidase only rescues HA. Non-HA products earn their place for durable structural work, but only in experienced hands and away from high-risk anatomy.
TL;DR:
- Reversibility is crucial in high-risk zones like the nose, glabella, and tear trough, requiring low G’ or low-cohesivity HA to allow quick hyaluronidase rescue if needed.
- High G’ HA fillers are best for deep structural support in areas such as the cheeks, jawline, and chin, with precise placement being vital for optimal results and safety.
- Cannulas significantly lower vascular occlusion risks compared to needles, especially when combined with experienced practitioners and slow injection techniques.
- Non-HA fillers like CaHA, PLLA, and PMMA provide longer-lasting results but are only suitable for experienced injectors due to their irreversibility and higher complication potential.
- Practitioners should source fillers from verified suppliers, track batch information, and store products per manufacturer guidelines to minimize risks of counterfeit and improper use.
Table of Contents
- Overview of filler families and their clinical properties
- What do G’, cohesivity and viscosity actually mean for injectors?
- Which filler and technique suit each treatment area?
- How should you choose between cannula, needle and layering technique?
- What are the main vascular risks and how do you manage them?
- What should practitioners check when sourcing and storing fillers?
- How Mirror Pharma clinical resources support safe, evidence-led practice
- Why staged, conservative treatment beats maximal correction
- Mirror Pharma: supplier support and clinical guidance for licensed practitioners
- Sources
- FAQ
Overview of filler families and their clinical properties
Every filler decision starts with family, not brand. HA fillers dominate clinical practice because they span a wide range of cohesivity and G’ values, covering almost every treatment area, and because they are reversible with hyaluronidase. That reversibility makes them the sensible first-line choice for less experienced injectors and for any zone with meaningful vascular risk, a point backed by a 2025 systematic review and practical guide to filler selection.
Non-HA options change the calculation. Calcium hydroxylapatite (CaHA) and poly-L-lactic acid (PLLA) stimulate collagen and offer longer-lasting volumisation, useful for patients wanting fewer sessions over a year or two. PMMA is semi-permanent and sits at the far end of the durability spectrum. Fat grafting offers autologous, long-term volume but demands surgical skill and carries its own resorption unpredictability.
None of these non-HA options are reversible, so they belong in the hands of practitioners with the experience to place them correctly the first time, and rarely in zones like the glabella or nasal dorsum.
Decision factors clinicians should weigh before selecting a family:
- Desired longevity versus the patient’s tolerance for repeat visits
- Reversibility requirements, especially in higher-risk anatomy
- Patient comorbidities, including bleeding disorders or autoimmune conditions
- Skin thickness, laxity and dynamic movement in the target area
What do G’, cohesivity and viscosity actually mean for injectors?
G’ (elastic modulus) tells you how well a filler resists deformation under load. Cohesivity describes how strongly the gel particles hold together as one mass, and viscosity is the resistance to flow through a needle or cannula. In practical terms, a high G’ product stands up under muscular movement and tissue weight, so it belongs deep, often on or near bone. A low G’ product spreads and integrates smoothly into thin, mobile tissue, which is exactly what you want under moving lips or in fine superficial lines.
Clinical charts mapping G’ bands to anatomical planes have become standard reference material, and the practical logic holds up: high G’ correlates with periosteal placement, low G’ with superficial dermal placement.
A working checklist before you pick a product:
- What plane does this anatomy demand: periosteal, subcutaneous, deep or superficial dermal?
- How much does this area move, and will a stiff product create lumps under animation?
- What longevity does the patient realistically want, balanced against reversibility needs?
- What is the vascular risk profile of this specific zone?
Pro Tip: Keep a simple three-band mental model (high, medium, low G’) rather than memorising individual product specification sheets. It speeds decision-making in clinic without sacrificing accuracy.
Which filler and technique suit each treatment area?
Selecting by area means pairing rheology with the right plane and, just as importantly, the right instrument.
-
Lips. Use a smooth, cohesive HA with mid-to-low G’ so the product moves naturally with the orbicularis oris. Place it in the deep dermis or submucosal plane depending on whether you’re adding volume or defining the border, and inject conservatively; overfilling here is the single most common aesthetic complaint. A product page such as the HyaCorp LIPS dermal lip filler illustrates the specification data practitioners check before selecting a lip-specific gel.
-
Tear trough. This is a low-volume, low-risk-tolerance zone. Use a low-spread, low G’ HA placed deep to the orbicularis oculi, directly on or near periosteum. Superficial placement risks Tyndall effect, the bluish discolouration from light scattering through gel sitting too close to thin skin.
-
Medial cheek. Structural support belongs here. High G’ HA placed periosteally restores projection and indirectly lifts the midface and nasolabial fold.
-
Lateral cheek. This area wants contour, not scaffolding. A mid-G’ product placed subcutaneously blends more naturally along the zygomatic arch than a stiff periosteal bolus would.
-
Nasolabial folds and marionette lines. A layered approach works best: deep structural support first, then a superficial, low-G’ layer for camouflage. Cannula technique reduces vascular risk in this densely vascular region.
-
Jawline and chin. High G’ periosteal boluses give the projection and angularity most patients ask for, and the bone-level placement keeps the product stable under muscular movement from chewing and speech.
-
Temples. Use subcutaneous, cannula-delivered contouring for mild volume loss; deeper periosteal placement is reserved for more significant temporal hollowing, and only where the injector is confident of the vascular anatomy.
-
Nose. Periosteal or perichondrial micro-boluses only, by experienced injectors. The nasal and nasolabial regions carry some of the highest complication rates in the specialty, driven by dense, unpredictable vascular anatomy, according to a review of injection technique and complication risk.
-
Glabella. Avoid deep medial boluses altogether given the proximity to the supratrochlear vessels. If treatment is indicated, use small volumes of superficial HA with a hyaluronidase-ready protocol in place before you inject.
How should you choose between cannula, needle and layering technique?
Cannula reduces the odds of penetrating a vessel wall because the blunt tip tends to push vessels aside rather than pierce them. Retrospective cohort data cited in clinical reviews found 77% lower odds of vascular occlusion with cannula compared with needle, and 70% lower odds when the injector had more than five years’ experience, regardless of instrument, per the review of injection technique and complication risk.
Needle still earns its place for precise periosteal boluses where exact placement matters more than lateral spread. Common technique choices:
- Retrograde linear threading: withdraw while depositing, useful for even lines along the nasolabial fold
- Serial puncture: small aliquots at multiple points, suited to periosteal boluses in the chin or cheek
- Fanning and crosshatching: cannula-based spread techniques for broader subcutaneous contouring, such as the temple or lateral cheek
Staged layering, deep support followed by a later superficial session for camouflage, reduces overfilling risk and produces more natural midface results than trying to achieve both in one sitting, a pattern borne out in complication-risk literature.
Pro Tip: When in doubt about vascular anatomy in a new patient, default to cannula and a smaller aliquot than you think you need. You can always add more at a review appointment.
What are the main vascular risks and how do you manage them?
Certain zones carry disproportionate risk because of dense or unpredictable vascular networks: the glabella (supratrochlear and supraorbital vessels), the nasal dorsum and columella (angular and dorsal nasal arteries), and the nasolabial fold (facial artery branches). The nose and nasolabial region show measurably higher complication rates than most other facial areas, a finding consistent across injection technique reviews.
Risk-reducing steps for licensed practitioners:
- Aspirate before injecting where technique allows, and inject slowly in small aliquots
- Favour cannula over needle in high-risk zones and stay in the correct anatomical plane
- Use ultrasound guidance for revision cases or complex anatomy where available
- Recognise blanching, severe pain or livedo pattern immediately as signs of possible occlusion
- Treat suspected vascular occlusion with high-dose hyaluronidase without delay, and escalate to urgent ophthalmology or vascular referral if vision or tissue viability is threatened
Cannula use alone cut occlusion odds substantially in one retrospective cohort. Combined with over five years of injector experience, both factors independently reduced the odds of vascular events, underlining why technique and training matter more than product choice alone. HA remains the safer starting point precisely because hyaluronidase can dissolve it when things go wrong, an option simply unavailable with CaHA, PLLA or PMMA.
What should practitioners check when sourcing and storing fillers?
Counterfeit and grey-market product remains a real governance risk in aesthetics. Buy only from suppliers who can demonstrate batch traceability, verify practitioner credentials before dispatch, and provide documented storage guidance.
- Confirm supplier verification processes and request batch numbers on every order
- Store products according to manufacturer guidance and monitor after-opening shelf life
- Record lot numbers, informed consent, clinical photographs and a follow-up plan for every patient
- Restrict purchase and use strictly to licensed practitioners under applicable prescribing rules
How Mirror Pharma clinical resources support safe, evidence-led practice
Mirror Pharma publishes clinical guides alongside its product pages specifically to help licensed practitioners make these calls with less guesswork.
- Hyaluronic acid fillers: a safety guide for practitioners covers reversal protocols and risk reduction in practical terms
- Product pages, including the HyaCorp FACE dermal filler listing, give verified practitioners the rheology and handling data needed before ordering
- Mirror Pharma operates as a verified B2B supplier, restricting sale to qualified aesthetic professionals with the compliance checks that status requires
Why staged, conservative treatment beats maximal correction
Conventional wisdom pushes for dramatic single-session results. The evidence points the other way: staged layering with conservative volumes, reversible HA in higher-risk zones, and disciplined case audit produce more natural outcomes and fewer complications than one aggressive sitting ever will. Document everything, keep training current, and treat again only when the tissue calls for it.
— Rizwan
Mirror Pharma: supplier support and clinical guidance for licensed practitioners
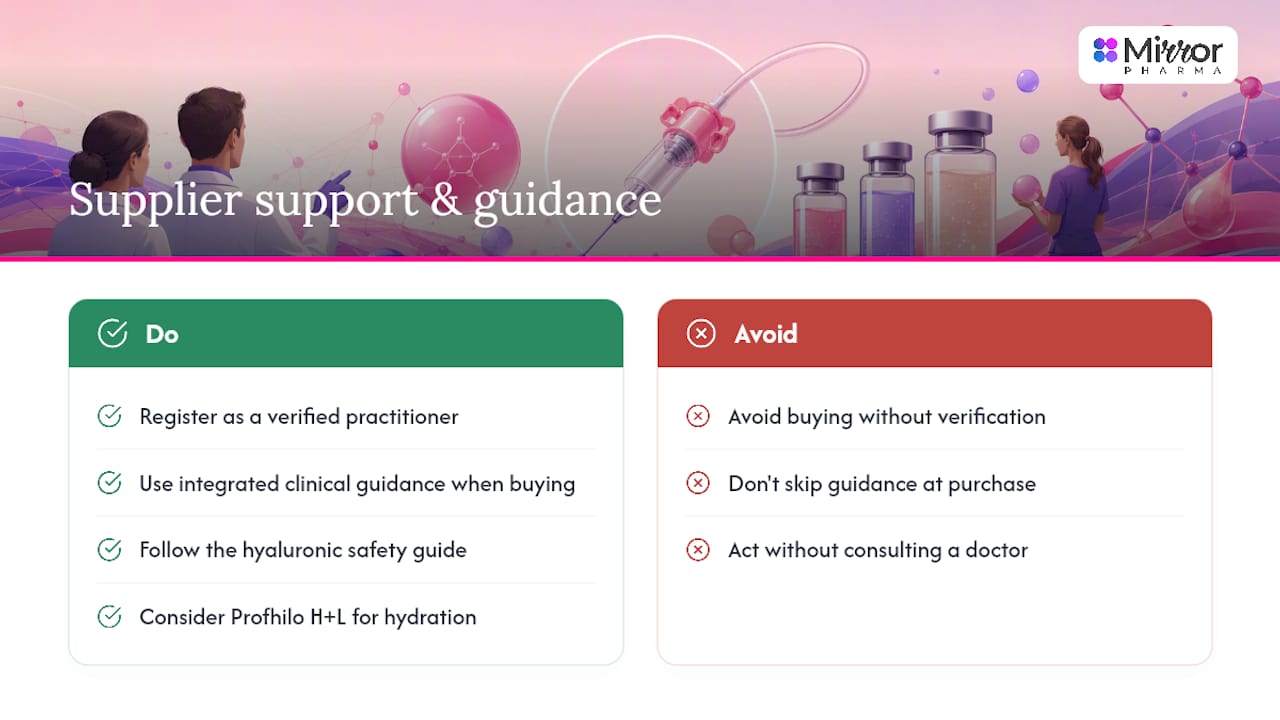
This supplier provides traceable batches with clinical guidance integrated into the buying process rather than added afterwards. Every dermal filler, skin booster and consumable listed is intended for verified, licensed practitioners.
Beyond the product catalogue, Mirror Pharma’s clinical guides, including the hyaluronic acid filler safety guide, give practitioners a reference point for reversal protocols and risk-reduction practice alongside procurement. If skin quality rather than structural volume is the goal for a given patient, the Profhilo H+L range is worth reviewing as a hydration-focused option. To register as a verified practitioner and browse the full clinical product range, visit Mirror Pharma.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- A practical guide to selecting facial fillers. Journal of Cosmetic Dermatology. 2025
- Facial fillers — Mayo Clinic overview
FAQ
What is the best filler for older skin?
There is no single best filler for older skin; ageing patients often need a combination of high G’ HA for deep structural loss at the cheek and jawline plus a lower G’ product for superficial volume, since bone resorption and skin laxity usually coexist.
What is the most painful area to get fillers?
The lips are widely reported as the most painful treatment area because of dense nerve supply, though pain tolerance varies significantly between patients and depends heavily on technique and anaesthesia.
Which filler looks most natural?
Lower G’, highly cohesive HA fillers placed in the correct superficial plane tend to give the most natural look in mobile areas like the lips and fine lines, while higher G’ products look natural only when placed deep enough to mimic bone rather than sitting visibly under thin skin.
What is the riskiest place for fillers?
The nose and glabella carry the highest vascular risk because of dense, unpredictable arterial anatomy, and complications in these zones can progress to skin necrosis or, rarely, vision loss if an occlusion goes unmanaged.